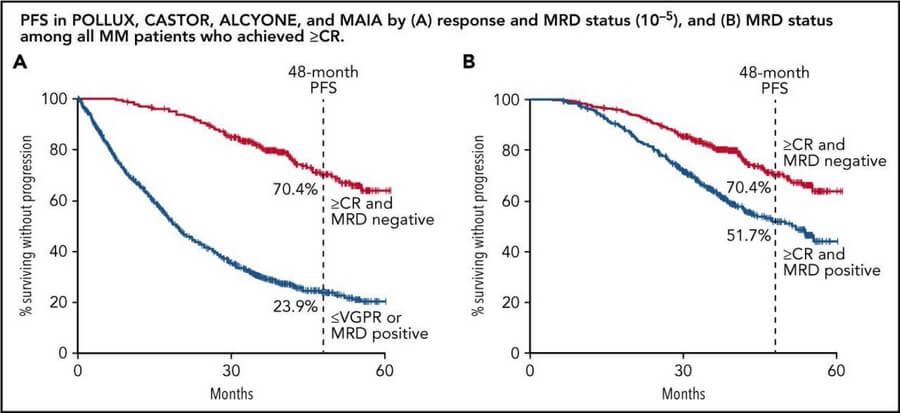
Prognostic value of minimal residual disease negativity in myeloma: combined analysis of POLLUX, CASTOR, ALCYONE, and MAIA

Author(s): Michele Cavo 1, Jesus San-Miguel 2, Saad Z Usmani 3, Katja Weisel 4, Meletios A Dimopoulos 5, Hervé Avet-Loiseau 6, Bruno Paiva 2, Nizar J Bahlis 7, Torben Plesner 8, Vania Hungria 9, Philippe Moreau 10, Maria-Victoria Mateos 11, Aurore Perrot 12, Shinsuke Iida 13, Thierry Facon 14, Shaji Kumar 15, Niels W C J van de Donk 16, Pieter Sonneveld 17, Andrew Spencer 18, Maria Krevvata 19, Christoph Heuck 19, Jianping Wang 20, Jon Ukropec 21, Rachel Kobos 19, Steven Sun 20, Mia Qi 20, Nikhil Munshi 22 23
Source: 2022 Feb 10;139(6):835-844. doi: 10.1182/blood.2021011101.

Dr. Lucio Gordan's Thoughts

MRD status in MM has unquestionable prognostic informational value, however many questions remain as how to address positive / negative MRD results. Should we de-escalate or stop Rx? When? Can we escalate Rx if + MRD? Which regimen, how long? It will be another few years till objective data are available. I do see value in at least having identification of clonality established upfront for tracking.

KEY POINTS

  • Patients who are MRD negative with ≥CR have improved PFS, regardless of therapy, vs those who do not reach CR or are MRD positive.
  • Daratumumab-based therapies lead to higher rates of ≥CR with MRD negativity compared with the standard of care.

VISUAL ABSTRACT

Combined analysis of POLLUX, CASTOR, ALCYONE, and MAIA

ABSTRACT

We explored minimal residual disease (MRD) in relapsed/refractory multiple myeloma (RRMM) and transplant-ineligible (TIE) newly diagnosed multiple myeloma (NDMM) using data from 4 phase 3 studies (POLLUX, CASTOR, ALCYONE, and MAIA). Each study previously demonstrated that daratumumab-based therapies improved MRD negativity rates and reduced the risk of disease progression or death by approximately half vs standards of care. We conducted a large-scale pooled analysis for associations between patients achieving complete response or better (≥CR) with MRD-negative status and progression-free survival (PFS). MRD was assessed via next-generation sequencing (10−5 sensitivity threshold). Patient-level data were pooled from all 4 studies and for patients with TIE NDMM and patients with RRMM who received ≤2 prior lines of therapy (≤2 PL). PFS was evaluated by response and MRD status. Median follow-up (months) was 54.8 for POLLUX, 50.2 for CASTOR, 40.1 for ALCYONE, and 36.4 for MAIA. Patients who achieved ≥CR and MRD negativity had improved PFS vs those who failed to reach CR or were MRD positive (TIE NDMM and RRMM hazard ratio [HR] 0.20, P < .0001; TIE NDMM and RRMM ≤2 PL HR 0.20, P < .0001). This benefit occurred irrespective of therapy or disease setting. A time-varying Cox proportional hazard model confirmed that ≥CR with MRD negativity was associated with improved PFS. Daratumumab-based treatment was associated with more patients reaching ≥CR and MRD negativity. These findings represent the first large-scale analysis with robust methodology to support ≥CR with MRD negativity as a prognostic factor for PFS in RRMM and TIE NDMM. These trials were registered at www.clinicaltrials.gov as #NCT02076009, #NCT02136134, #NCT02195479, and #NCT02252172.

Author Affiliations

1IRCCS Azienda Ospedaliero-Universitaria di Bologna, Istituto di Ematologia “Seràgnoli”, Dipartimento di Medicina Specialistica, Diagnostica e Sperimentale, Università di Bologna, Bologna, Italy. 2Clínica Universidad de Navarra, Centro de Investigación Medica Aplicada (CIMA), IDISNA, CIBER-ONC, Pamplona, Spain. 3Levine Cancer Institute/Atrium Health, Charlotte, NC. 4Department of Oncology, Hematology and Bone Marrow Transplantation with Section of Pneumology, University Medical Center Hamburg-Eppendorf, Hamburg, Germany. 5National and Kapodistrian University of Athens, Athens, Greece. 6Unite de Genomique du Myelome, IUC-Oncopole, Toulouse, France. 7Arnie Charbonneau Cancer Research Institute, University of Calgary, Calgary, AB, Canada. 8Vejle Hospital and University of Southern Denmark, Vejle, Denmark. 9Clinica Medica São Germano, São Paulo, Brazil. 10Hematology, University Hospital Hôtel-Dieu, CHU Nantes, Nantes, France. 11University Hospital of Salamanca/IBSAL/Cancer Research Center-IBMCC (USAL-CSIC), Salamanca, Spain. 12Hematology Department, University Cancer Institute IUCT, Toulouse, France. 13Department of Hematology and Oncology, Nagoya City University Graduate School of Medical Sciences, Mizuho-ku Nagoya, Japan. 14University of Lille, CHU Lille, Service des Maladies du Sang, Lille, France. 15Department of Hematology, Mayo Clinic Rochester, Rochester, MN. 16Department of Hematology, Amsterdam University Medical Center, Vrije Universiteit Amsterdam, Amsterdam, The Netherlands. 17Erasmus MC, Rotterdam, The Netherlands. 18Malignant Haematology and Stem Cell Transplantation Service, Alfred Health-Monash University, Melbourne, Australia. 19Janssen Research & Development, LLC, Spring House, PA. 20Janssen Research & Development, LLC, Raritan, NJ. 21Janssen Global Medical Affairs, Horsham, PA. 22Dana-Farber Cancer Institute, Harvard Medical School, Boston, MA; and. 23Veterans Administration Boston Healthcare System, West Roxbury, MA.

Leave a Comment

Your email address will not be published. Required fields are marked *

Related Articles

Talquetamab–Daratumumab in Relapsed or Refractory Myeloma

A total of 287, 287, and 290 patients were assigned to the Tal-DP, (tal with dara and pomalidomide) Tal-D(Tal with dara) , and DPd (dara, pom and dex) groups, respectively. Progression-free survival (PFS) was 81.3% for TalDP and 77.6 % for Tal D compared to 51.2% for DPd. The overall response was higher with Tal-DP and Tal-D than with DPd (88.2% and 88.5% vs. 77.6%), as was complete response or better (71.1% and 69.0% vs. 34.5%) and measurable residual disease–negative complete response (52.3% and 46.3% vs. 15.9%) (P<0.001 for all comparisons). Overall survival at 24 months was 89.2% with Tal-DP, 87.9% with Tal-D, and 79.1% with DPd. Tal DP had less fatality secondary to adverse events (1.8%) vs Tal d 4% and DPd 4.6%. We will see more studies with cellular therapy combinations now and it seems promising, esp. with better control of toxicity.

Read More »

Talquetamab–Daratumumab in Relapsed or Refractory Myeloma

Talquetamab plus daratumumab (with or without pomalidomide) delivered a striking progression-free survival (PFS) benefit over daratumumab plus pomalidomide and dexamethasone (DPd) in early-line relapsed/refractory myeloma, 24-month PFS of ~80% versus 51% and MRD-negative CR rates three times higher than the control arm. OS trending favorably but not yet mature. The GPRC5D toxicity profile is manageable but distinct, counsel patients upfront on taste changes, skin/nail effects, weight loss, and watch closely for ataxia/balance issues, which warrant holding the drug and early neurology involvement.

Read More »